
This post was last updated on September 13, 2026.
Dengue fever, increasingly in the news in North America and Europe, is caused by a mosquito-borne virus. About half of the world’s population is now at risk of dengue, with an estimated 100 to 400 million infections occurring each year. Each year it also kills many thousands of people, leading the World Health Organization (WHO) to describe it as one of the top ten threats to global health. Yet for most people who haven’t lived or travelled to the areas it most affects, it’s an unfamiliar virus.
I am sharing resources about dengue for several reasons. First, because the virus’s footprint continues to expand as our planet’s weather patterns change and mosquito areas change with it. It is now cropping up in parts of Europe and North America, where people are less knowledgeable about the condition. This includes a sustained outbreak of locally acquired cases in Florida in 2026, which has its own section below. Second, because, as I note below, dengue antibodies can cross-react with SARS-CoV-2, the virus that causes Covid. Covid remains a health issue worldwide that impacts our immune systems, even if we aren’t in the early phases of a pandemic.
And finally because it changed my life — and not for the better, either.

For my story of how I got dengue fever in Vietnam, please see my Legal Nomads post here.
The disease is present in more than 100 countries per the WHO, which also notes that cases have surged in recent years. 2024 was dengue’s worst year on record; WHO’s global epidemiological overview recorded 14,434,584 cases, including 52,738 severe cases and 11,201 deaths, across all six WHO regions, with the Region of the Americas accounting for more than 90% of the global total and Brazil alone reporting over 10 million cases.
Its dengue dashboard allows you to track the virus worldwide.
At the time of this update, 2026 has been a quieter year thus far in the Americas. There has been a 58% decline in cases compared with the same period in 2025, and cases are also 65% below the five-year average. That said, dengue’s spread and data are not always linear. Some years see a surge in a different area than the years preceding it, which for 2026 appears to be a newer outbreak in Florida.

Why the differences in spread? Several factors are at play, from changing distribution of the vectors themselves (primarily the Aedes aegypti and Aedes albopictus mosquitoes), as well as warming climates, record rainfall, and humidity. While the viral fever is common in parts of Asia and the Americas, global warming has affected the reach of the mosquitoes that spread it.
Take France as an example: when I first wrote about dengue, France reported locally transmitted cases in 2022, with 66 cases by year-end (a record). In 2025, local transmission was confirmed in Nouvelle-Aquitaine, Grand Est, and Bourgogne-Franche-Comté, three regions that had never recorded local transmission before.
Presently, there is no cure for dengue fever — only management and prevention.
Dengue fever basics: serotypes, symptoms & immunity
There are four well-established dengue fever serotypes: DENV-1, 2, 3, and 4. A fifth serotype, DENV-5, was reported in 2013 from a sylvatic (forest-cycle) sample collected in Malaysia, but DENV-5 has never been formally confirmed or recognized as a human serotype. Manifestation of symptoms may differ depending on the type you contract.
I was told often in Asia that recovery from one strain of dengue may offer lifelong immunity against that strain, and after two infections you “may be immune to all serotypes”. However, in 2023 a study from Nicaragua shed some light on this long-standing belief. The results contradicted the conventional wisdom that people can become immune to the dengue virus for the rest of their lives after repeated infections. Instead, the study found that antibody responses can wane over time. Infection with one serotype provides some long-term protection against that serotype, but protection against the other three is only partial and temporary. A subsequent infection with a different serotype can carry a higher risk of severe dengue. The timing between infections and the particular sequence of serotypes may also influence this risk.
Eradicating the mosquito-borne disease is likely an impossibility, though many scientists are racing to find solutions.
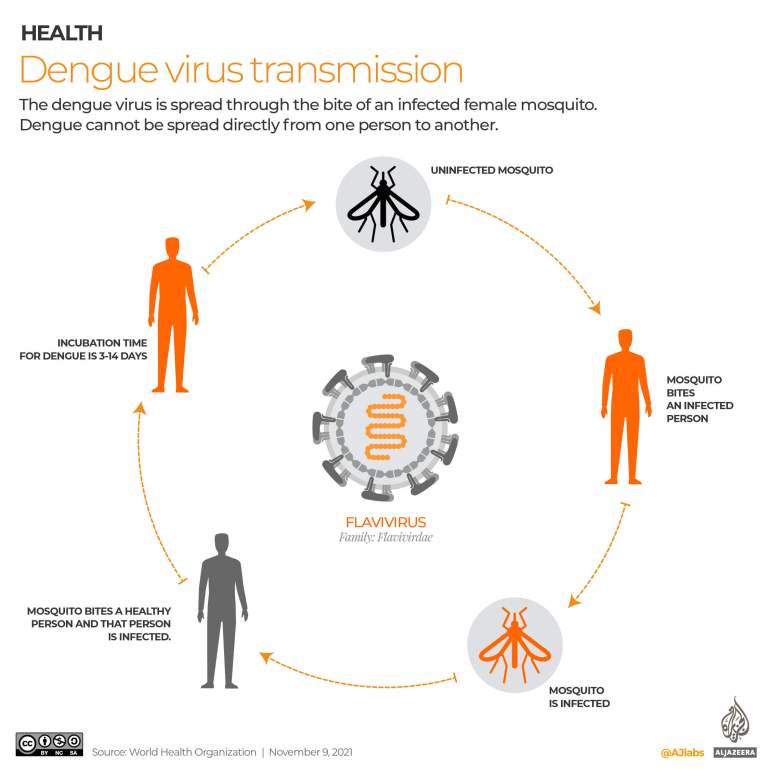
How dengue virus transmits between mosquitoes and humans. Via Al Jazeera
Dengue’s incubation period is between 3 to 14 days, so it’s difficult to backtrack to exactly what mosquito bit you. In my case, I have a very good idea. I was outside on a phone call and came inside so bitten up that I almost vomited. It was less than a week later that my symptoms started.
Symptoms of dengue fever
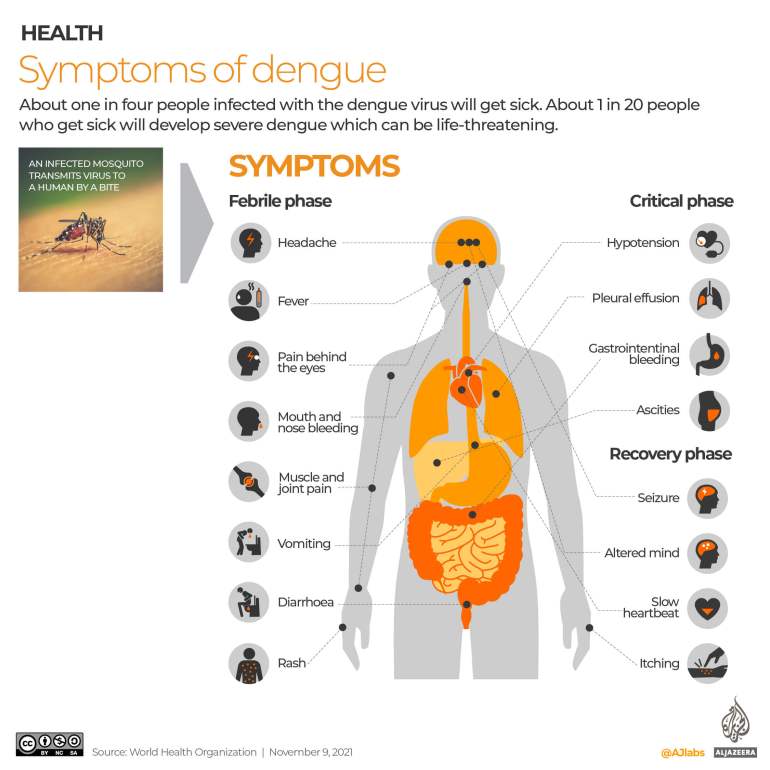
The most common symptoms of dengue fever are:
- A sudden, high fever
- Feeling general malaise (like the flu)
- Severe head pain
- Severe pain behind the eyes
- Joint pain
- Musculoskeletal pain (muscle and/or bone pain): there’s a reason this virus is sometimes referred to as ‘breakbone fever’ or ‘bone break fever’. It can be quite painful, especially for me in my legs/shins.
- Rash: the rash usually occurs several days after symptoms begin, and is a flat rash of red dots on the skin. It does not blanch under pressure, and small islets of normal skin appear throughout — sometimes described as islands of normal skin in a sea of red dots. See these photos for examples.
- Mild bleeding manifestations (e.g., nose or gum bleed, smaller dotted petechiae, or easy bruising)
- Low white cell count
- Loss of appetite
Dengue hemorrhagic fever (DHF) and “severe dengue”
In addition to concerns about waning immunity, there is also the issue of severe dengue. Dengue hemorrhagic fever (DHF) is an older term used in the WHO classification to describe a more serious dengue infection, but in 2009, WHO introduced a revised system with three categories: (1) dengue without warning signs, (2) dengue with warning signs, and (3) severe dengue. The change was made because the older DHF criteria did not capture all patients with clinically severe disease. “DHF” is still encountered in medical literature and in some countries, but “severe dengue” is the terminology used in current WHO guidance.
See below for symptoms of “severe dengue”.
From Science “When Dengue Strikes Twice“:
Many [people] who suffer repeat infections have it worse. They come down with dengue hemorrhagic fever and suffer massive internal bleeding and liver damage. Oddly, the virus causing dengue fever comes in four strains, and immunity to one seems to make infection by a second strain more dangerous.
The hunt is still on for why severe dengue is so severe. Researchers have investigated several possible mechanisms, including antibody-dependent enhancement and complex interactions between innate and adaptive immune responses, but conclusions remain incomplete.
Dengue hemorrhagic fever was recognized as a distinct severe clinical syndrome during epidemics in Southeast Asia in the 1950s. Today, severe dengue is in most of Asia, South and Southest Asia, and Central and South America, and is a leading cause of hospitalization and death in those regions.
Warning signs can appear as the fever begins to subside. They include severe abdominal pain or tenderness, persistent vomiting, fluid accumulation, lethargy or restlessness, bleeding, rapid breathing, and blood in vomit or stool. Doctors may also find a drop in platelet count and sometimes a rise in hematocrit.
Severe dengue can lead to shock or respiratory distress, severe bleeding, or severe organ impairment.
People with severe symptoms should get care right away.
A practical note about food: blueberries, blackberries, and other dark foods can sometimes change stool colour and make it harder to recognize gastrointestinal bleeding. But black or bloody stool during suspected dengue should not be assumed to be food-related even if you’re eating berries; seek medical assessment if this occurs.
Treatment and what to do if you suspect dengue fever
Obviously do NOT do what I did and simply go on with your life. I wish I’d had it diagnosed early, as dengue was the virus that began the process that led to a full derailing of my life.
There is currently no specific antiviral treatment routinely recommended for dengue; treatment is primarily supportive and focuses on symptom relief, maintaining fluid balance, and recognizing severe disease early.
Great, right?
The mainstay of treatment is still careful fluid management, something I did not have access to.
After going through what I did, the information I wish I had was:
- Go to a clinic and/or hospital and get tested for dengue fever.
- Stay adequately hydrated, but avoid deliberately drinking excessive amounts of fluid. People with warning signs or severe dengue may require carefully monitored intravenous fluids, because both inadequate fluid replacement and fluid overload can be dangerous.
- Avoid aspirin and nonsteroidal anti-inflammatory drugs (NSAIDs), such as ibuprofen and naproxen, because they can increase the risk of bleeding. Acetaminophen/paracetamol is generally preferred for fever and pain unless a healthcare professional advises otherwise.
- Consume electrolyte tablets or oral rehydration salts, though not in excess. I use NormaLyte for my electrolytes now.
- If symptoms progress, to seek IV hydration in a clinical setting.
Please also see my post about chronic pain for advice about managing pain long term, should you have the unfortunate reality that you need it like I did. Anecdotally, mast cell stabilizers or antihistamines were helpful for people in online groups, and very helpful for me to manage my nerve pain and other pain. You can refer to my mast cell activation resources page for more on that front.
The Pan American Health Organization has a 158-page guide called Guidelines for the Clinical Diagnosis and Treatment of Dengue, Chikungunya, and Zika that I have downloaded and is available as a PDF here.
Yes, you CAN get dengue fever more than once
Yes, as noted above, you can get dengue more than once.
There are four well-established serotypes (or strains) of the dengue virus: DENV-1, DENV-2, DENV-3, and DENV-4. It is possible to get infected by each serotype.
Protection against the infecting serotype is thought to be long-lasting, while protection against the other serotypes can wane over time.
It was initially thought that you were immune for life after getting one strain of dengue, but research in recent years has corrected that statement. A study that drew on a large cohort of highly exposed children and adults in Nicaragua (n = 4,478) found evidence of antibody boosting and waning both during and after major dengue and Zika epidemics, suggesting that immunity is not permanent.
As mentioned above, a subsequent infection with a different serotype can sometimes result in antibody-dependent enhancement (ADE), where pre-existing, non-neutralizing antibodies facilitate viral infection and may contribute to more severe disease. This means that if someone has been infected with dengue, it is important to try and avoid another infection.
“Long dengue”, genetics, and the lingering effects of an infection
While many of my friends have come out just fine after a dengue infection, lingering effects like the ones I experienced are very widely documented.
- Depression and anxiety can occur after the acute infection wanes, likely due to systemic inflammation. See this study about anxiety/depression and severity of dengue symptoms.
- Lingering fatigue: Fatigue can persist after the acute illness has resolved. A 2024 systematic review/meta-analysis found fatigue prevalence of about 59% during and after dengue, and post-infectious fatigue incidence of 20%, although the studies were heterogeneous. A 2026 meta-analysis also specifically examined post-dengue fatigue and depression. It found associations between post-dengue fatigue, the female sex, myalgia (muscle pain and aches that can involve muscles, ligaments, tendons, and fascia), and having severe dengue, although the evidence base remains limited.
- Genes and gene expression: geneticists have begun to look at whether your gene composition could affect the severity of the infection or whether it creates sufficient inflammation to “express” genes you may already have and create a genetic cascade.
- Autoimmune marker changes to titers for C3/C4, rheumatoid factor (RF), C-reactive protein (CRP), antinuclear antibodies (ANA), and immune complex (IC).
- Developing mast cell dysfunction following dengue fever is what happened to me, but there is not much research here. Laboratory research has found that dengue virus can directly stimulate human mast cells to produce inflammatory chemokines, which can occur without significant mast cell degranulation. Mast cells may contribute to the early immune response to dengue. I’ve written an egregiously long page about tackling mast cell disease and/or increased allergic reactions, as well as increased sensitivity to environmental triggers: it’s here.
- In rare cases, dengue fever can also affect the nervous system and lead to conditions such as myositis, Guillain-Barré syndrome, or hypokalemic paralysis.
- In 2023, the American CDC updated its post-viral illness page to list out viruses that can lead to long-term symptoms in the body and included dengue as one of the viruses known to do so.
One significant area of recent research concerns why dengue severity varies so dramatically from person to person. Newer findings point to genetic ancestry as a key factor. Researchers at the University of Pittsburgh and Instituto Aggeu Magalhães in Brazil have for the first time linked the extreme variability in severity of dengue between individuals to the influence of genetic ancestry on inflammatory responses in the skin.
The team exposed human skin explants from donors of European or African ancestry to dengue virus and found that inflammatory responses promoting virus replication and spread are influenced by genetic background, with immune activity increasing with greater European ancestry.
Lead author Dr. Priscila Castanha, an assistant professor of infectious diseases and microbiology at Pitt’s School of Public Health, published her findings in a paper entitled “Genetic ancestry shapes dengue virus infection in human skin explants“, noting that their findings help “explain a longstanding epidemiological puzzle” about reports of a protective effect of African ancestry against severe dengue
The mechanism, as the team described it, is a kind of “friendly fire”: in samples from donors of European ancestry, myeloid cells mobilized to fight the virus, then themselves became infected, and subsequently migrated out of the skin — similar to how they would travel through the bloodstream into lymph nodes, spreading infection further. In skin samples from donors with higher African ancestry, this cascade was significantly dampened.
The researchers suggest the findings may have implications for how dengue vaccines are designed and assessed, noting that genetic ancestry may affect the way different populations respond to dengue vaccines, which are weakened viruses delivered via the skin. As Dr. Castanha noted, “evolution has made its mark on everyone’s DNA.”
Dengue fever makes mosquitoes bite more
A fascinating bit of science that may also affect transmission: a study several years ago found that being infected with dengue fever can cause you to produce bacterium in the skin that makes you more attractive to mosquitoes. In addition, studies have found dengue makes mosquitoes that are infected with the virus bite more than mosquitoes that are uninfected.
This biting-the-host stuff is called “blood-feeding behaviour”, and blood-feeding behaviour is a key factor in how mosquitoes spread the disease.
Earlier studies on how dengue virus infection changes the way mosquitoes feed haven’t been that conclusive. But in 2022, researchers took a broader, multidisciplinary approach using a variety of tools like high-resolution video to try and analyze the differences in blood-feeding with mosquitoes that had dengue, and those that did not. In a study in PNAS called Dengue virus infection modifies mosquito blood-feeding behavior to increase transmission to the host, the research team sought to understand transmission to then look at the reasons why these changes happen. And, more promisingly, if they can identify a gene or protein that causes this, they may be able to protect against dengue from that angle!
“We found that the dengue virus increases mosquito attraction to the mammalian host and the number of mosquito bites,” says Ashley St. John, associate professor from Duke NUS’ Emerging Infectious Diseases (EID) Programme, and senior coauthor of the study. The higher attraction to the mammalian host increases the chances of the mosquito to bite, while more bites increase the number of transmission events because each bite results in the transmission of the virus.
Awesome. So, essentially: dengue-infected mosquitoes are extra dangerous because they not only carry a pathogen, but spread it more via extra “bites”.
The increase in bites isn’t due to a psychological drive to infect, but rather because the mosquitoes seem to be unable to find blood vessels to feed from as easily, so they bite multiple times to try and get one, thus releasing their dengue-filled saliva into the body more than those mosquitoes that are uninfected (and can find vessels more easily).
The video below shows footage that was then analyzed by computer software, to understand the ways that blood-feeding differed between dengue-mosquitoes and non-dengue mosquitoes.
This is especially an issue, as a recent research article in Science concluded that mosquitoes in Southeast Asia are starting to be resistant to insecticides that countries use to help control the spread of the disease.
Just what we need.
Asymptomatic dengue? More common than we thought.
Interestingly, a 2023 study posited that asymptomatic people are responsible for a far larger amount of dengue cases than previously realized. The study results found that 8% of areas where people gathered represented more than 50% of all the infections during an outbreak. Of those spaces, 74% of infected cases were asymptomatic. These are people who have no symptoms, and continue to live their lives unknowingly infecting mosquitoes that bite them — mosquitoes that then go and bite other people and infect them, too.
This study shows that while approaches have historically been reactive (treat people with symptoms; spray / net areas with known outbreaks), we need to also think about containing outbreaks proactively given the role of superspreaders who have no symptoms.
Per Gonzalo Vazquez-Prokopec, one of the study authors:
“Our findings show that any public health intervention that focuses on responding to symptomatic cases of dengue is going to fail to control an outbreak. Symptomatic cases represent only the tip of the iceberg.“
Dengue’s global spread
Per the American CDC, dengue is endemic throughout the tropics, subtropics, Central and South America, the Caribbean, and Southeast Asia. Risk now includes the USA, where sporadic local cases have popped up in Florida, Hawaii, and Texas along the border with Mexico, as well as parts of Europe.

Although the geographic distribution of dengue is similar to that of malaria, dengue is more of a risk in urban and residential areas than is malaria.
For up-to-date information of outbreaks in real-time, see the thorough DengueMap. I’ve included a screenshot above.
As of mid-March 2026, the WHO’s Western Pacific Regional Office continued to track active dengue transmission across many countries. In Cambodia, as of epidemiological week 10 of 2026, a total of 4,338 dengue cases were reported — a significant increase from the same period in 2025, when 1,392 cases were reported. Vietnam has seen a two-fold increase in cumulative cases compared to the same period in 2025, with over 27,000 cases reported by early March 2026, and Malaysia had already recorded over 11,000 cases with nine deaths in the first nine weeks of the year.
The spread in the Americas has, as mentioned above, gone the other way in 2026: there has been a decline in case counts in the region, which are well below the five-year average.
Singapore’s 2026 serotype profile as of February showed DENV-2 as dominant at 71%, with DENV-3 at 19.4%, DENV-1 at 3.2%, and DENV-4 at 6.5%. For the most current surveillance data in the Western Pacific region, the WHO publishes these situation updates regularly, and they are publicly accessible.
In 2026, the American CDC issued a travel notice of an increase in dengue-infected travellers returning to the USA, especially from people returning from Afghanistan, Bangladesh, Bolivia, Colombia, Cook Islands, Cuba, Guyana, Maldives, Mali, Mauritania, New Caledonia, Pakistan, Samoa, Sudan, Timor-Leste, and Vietnam. Locally acquired cases in the USA are still a small percentage of total caseload, but they are climbing year-over-year. In 2026 that increase has been most visible in Florida thus far. Please see the new section I added in 2026, below. USA cases can be tracked here.
What about Chikungunya and Zika?
Dengue, Zika and Chikungunya are transmitted primarily by Aedes mosquitoes. Aedes aegypti is the principal vector for dengue, while Aedes albopictus can also transmit the virus. Aedes aegypti mosquitoes will happily breed in even the shallowest of water sources; it is disturbingly efficient at multiplying, and happily takes up residence in cities where it can bite many people in a row. If it feeds on a person with dengue, then the virus incubates in the mosquito’s belly, migrates to its salivary glands, and is injected during its next bite.
Also, I regret to inform you that it is possible to obtain more than one mosquito-borne disease (co-infection) from the same mosquito.
An American reader living in Manila for many years kindly sent me her story of both dengue and Chikungunya. In her words:
“My experience was horrendous. Very, very similar to what you went through. The reason I am emailing you is to let you know it’s very likely you had both dengue and Chikungunya. The mosquito that carries dengue can also carry Chikungunya. If you get bit by a mosquito carrying both, you can be infected by both dengue and Chikungunya at the same time. This is what happened to me.“
The symptoms for both diseases are quite similar, per the American CDC, and Chikungunya has so far been found well beyond its usual locations and as far as Texas, Spain, France, Mexico, and more, including the Caribbean where it was first detected in the Americas. Florida’s own 2026 surveillance shows us how viruses travel together; alongside its dengue numbers, the state has recorded 60 travel-associated Chikungunya cases so far this year, 42 of them linked to travel from Cuba.
Dengue and Chikungunya can cause similar acute symptoms, including fever, headache, muscle and joint pain, and rash. Dengue is more strongly associated with potentially life-threatening bleeding and organ involvement, whereas Chikungunya is particularly notable for severe and sometimes prolonged joint pain. Although death from Chikungunya is uncommon, severe and fatal cases can occur.
Given that the three illnesses offer up similar symptoms, I wanted to devote a part of this post to Zika as well. The virus didn’t just appear in 2016. In fact, it’s been around for a long time. First identified in monkeys in Africa (Uganda to be exact) in the late 1940s, it spread to humans around the early 1950s. The WHO documented the first case in 1952.
Zika is reported to produce milder symptoms, and many infections are asymptomatic. When symptoms do occur, they are cited as a less painful version of the rash, headaches, pain and fever mentioned above. Symptoms usually occur 3 to 12 days following a bite from an infected mosquito. There’s also no vaccine or treatment for the virus, so doctors just work on controlling and alleviating its symptoms.
Zika’s mildness in most adults is not a given. I’m someone who is often a health outlier, and there are exceptions to pay attention to here as well. Infection during pregnancy can cause microcephaly (a smaller than normal head size), along with other congenital malformations, preterm birth and miscarriage. In adults and children it is also associated with Guillain-Barré syndrome. This is why Zika became a global emergency in 2016 when the WHO declared Zika-related microcephaly a Public Health Emergency of International Concern in February of that year, following a large epidemic in Brazil. It lifted the emergency that November once the causal link to congenital malformations was confirmed — a longer-term plan was needed to manage the global response. Global case counts have declined since 2017, but the risk in pregnancy is the reason travel advice for Zika is still far more cautious than its symptom list above suggests.
Warming planet, moving mosquitoes
As I mentioned in the introduction, with a warming planet, mosquitoes have proliferated, and mosquito-borne illnesses have swept across the globe.
Each year seems to be a banner year for those illnesses, with more and more mainstream news coverage about dengue, Chikungunya and Zika.
Said climate scientist Winston Chow from the College of Integrative Studies at Singapore Management University, “constant weather extremes create the perfect breeding conditions for mosquitoes“. Climate changes begets more viral emergencies, and changing temperatures leads to new patterns in global dengue transmissions:

At the time of writing my original piece, I had friends in Siem Reap, Cuba, Rio de Janeiro, and Delhi who had dengue at the same time and in very disparate places. One of the hardest symptoms following dengue is the depression and anxiety that follow.
A 2025 study entitled “Disentangling climate’s dual role in dengue dynamics: A multiregion causal analysis study” unveiled new insights into how weather influences the spread of dengue fever as well. The paper identified temperature and rainfall as critical factors driving the global surge in dengue cases and offered actionable strategies for mitigating the disease’s impact, though I will say it’s not a surprise that these two factors play in. We know these mosquitoes love wet climates, and we know climate change is making some places hotter and wetter. (And others drier, of course.) The study focused on 16 areas in the Philippines, selected for their diverse climatic conditions, to examine how temperature and rainfall jointly affect dengue dynamics. The most important factor ended up being variation in dry season length: in areas with low variation in dry season length, rainfall tended to flush out stagnant water, reducing mosquito breeding sites and suppressing dengue transmission. But in areas with high variation in dry season length, sporadic rainfall created new breeding sites and weakened the flushing effect, driving an increase in mosquito populations and dengue cases.
The most direct evidence yet of climate change driving a specific dengue outbreak comes from a March 2026 study published in One Earth. Researchers from Stanford University and other institutions traced Peru’s 2023 dengue outbreak directly to cyclone conditions, finding that 60% of cases stemmed from extreme rainfall and heat associated with Cyclone Yaku and a coastal El Niño. Lead author Mallory Harris, now a postdoctoral scholar at the University of Maryland, framed the urgency clearly: the health impacts of climate change “aren’t something we’re waiting for. They’re happening now.”
The numbers behind the paper’s findings are fairly intense: more than 22,000 people likely would not have contracted dengue in the absence of the unusually extreme weather conditions brought by the cyclone. And climate modelling puts this in a longer-term context: extreme precipitation conditions like those seen in 2023 are now 31% more likely in northwestern Peru than they were before industrialization, and when combined with warming temperatures, the probability of climate conditions like those that fuelled the 2023 dengue epidemic has nearly tripled.
The study is the first to look at one specific infectious disease outbreak and one specific extreme weather event to rigorously attribute a share of cases to climate, calling it “a big step forward for the methods of the field.”
The practical implication for health systems is that climate-preparedness and epidemic preparedness are now inseparable. The problem is, as we’ve seen in North America, that climate targets are no longer the focus due to increasingly acute geopolitical threats. Still, even smaller actions like targeted mosquito control and vaccination in high-risk urban districts, along with investments in urban flood resilience (like better drainage, sturdier housing, and more reliable water infrastructure) would truly help.
As extreme weather events become more frequent with climate change, scientists stress the need to think strategically and act decisively to prevent mosquito-borne epidemics.
I just don’t know that we will.
Wolbachia-infected mosquitoes reduce dengue infections
An interesting solution for the dengue problem: instead of only looking for a vaccine to help prevent the disease, what if the mosquitoes themselves could be defanged? There have been reports of genetically modified mosquitoes released to test whether they lower overall dengue case numbers. Another example of that is a programme that began as a pilot project in Yogyakarta, Indonesia, where the mosquitoes were purposely infected with a bacterium commonly found in the insect world.
The bacterium, Wolbachia, was first discovered in 1924 and is found in mosquitoes — just not the Aedes aegypti.
From a June 10, 2021 piece by Ed Yong:
They’ve loaded the mosquitoes with a bacterium called Wolbachia, which prevents them from being infected by dengue viruses. Wolbachia spreads very quickly: If a small number of carrier mosquitoes are released into a neighborhood, almost all of the local insects should be dengue-free within a few months. It’s as if Utarini’s team vaccinated a few individuals against a disease, and soon after the whole population had herd immunity.
and
The team found that just 2.3 percent of feverish people who lived in the Wolbachia release zones had dengue, compared with 9.4 percent in the control areas. Wolbachia also seemed to work against all four dengue serotypes, and reduced the number of dengue hospitalizations by 86 percent.
While the Wolbachia strategy is not immediate, it blocks dengue infections in a few different ways that lead the mosquitoes to be less likely to carry dengue and thus transmit it to people. In 2023, three cities in Colombia saw a dramatic decline in the incidence of dengue infections after introducing the mosquitoes carrying Wolbachia. In neighbourhoods where the Wolbachia mosquitoes were well established, dengue incidence dropped by 94–97%.
As of 2026, the results have held up.
Niterói, Brazil houses the country’s longest-running city-wide deployment, Wolbachia was still established in 95% or more of the local mosquito population 4 years after releases stopped, and up to seven years at the earliest release sites. Dengue incidence in the city was 89% below the pre-intervention levels for 2007 to 2016. And most promisingly, that protection was still around in 2024, which was the worst dengue year on record in the Americas.
Brazil has since adopted Wolbachia as national policy. Campo Grande was the first city under the new policy to get the Wolbachia mosquitoes, and the published results showed substantial reductions in dengue incidence across the city.
While exciting, this bacteria isn’t foolproof. Rio de Janeiro and Niterói are only 14 kilometres apart with a bridge separating them. The two cities have very similar climates and environments, but very different outcomes for Wolbachia. While Niterói had success and a drop in dengue fever, in Rio Wolbachia’s foothold was uneven and didn’t keep going once releases of the mosquitoes ended. Researchers think that the differences are potentially due to weaker integrated vector management and what Wolbachia does to the mosquitoes themselves; releasing the mosquitoes isn’t always enough on its own.
Also, the Wolbachia strain is heat-sensitive. Just 7 days of fluctuating 30–40°C temperatures cut Wolbachia to less than 0.1% of normal levels with only partial recovery. So if the world keeps warming the way it has been, these results may not bear out as promisingly as they have thus far.
With all that said, Brazil has since expanded the Wolbachia programme, opening the world’s largest “mosquito biofactory” in Curitiba that can produce around 100 million eggs a week.
As of January 2026, Wolbachia releases worldwide have reached more than 16 million people across 15 countries.
Florida’s 2026 dengue fever outbreak
I received a lot of questions from readers in 2026 about the news out of Florida related to dengue, and as part of my annual update I have added a new section.
As of the time of writing, 2026 has been an unusually active dengue year for the state. According to the Florida Department of Health’s weekly arbovirus surveillance report for the week of August 30–September 5, 2026 (the most recent published as of this update), Florida has recorded 111 locally acquired dengue cases in 2026, alongside 160 travel-associated cases. That is an unusual jump from typical data; Florida saw 68 locally acquired cases in all of 2022, and 186 in all of 2023.
The current outbreak is concentrated in the Tampa Bay area. Hillsborough County alone accounts for 95 of the 111 locally acquired cases, with onset in July and August, making it the current epicentre at the time of writing this update. Miami-Dade (7 cases), Pinellas (5), Pasco (2), Orange and Palm Beach (1 case each) account for the rest. Pinellas County’s cases are also notable because they are the area’s first locally acquired dengue in more than 15 years.
Of the cases serotyped thus far, DENV-2 is dominant.
Travel-associated cases remain the larger share of Florida’s overall dengue burden, with Cuba as the leading source of imported cases, followed by Colombia.
Florida’s health department updates these numbers weekly, and because mosquito season typically runs into October or later, the 2026 totals will likely keep climbing before the year is out.
Standard mosquito-bite precautions apply: repellent, covering up at dawn and dusk, and emptying standing water around your house or wherever you’re staying. Unfortunately, these issues are here to stay.
SARS-CoV-2, Covid, and dengue fever
SARS-CoV-2’s worldwide spread has further weighed on countries where dengue fever is already an endemic population threat, primarily in tropical and subtropical regions of the world. But as discussed here, dengue is spreading more widely now. People do need to be aware of how these two viruses interact in the body.
Covid, the illness caused by the SARS-CoV-2 virus, and dengue share some symptoms. This has led to diagnostic challenges. Moreover, cross-reactivity of the body’s immune response to each of these infections is something on scientists’ radar. There is emerging evidence of immunological cross-reactivity between SARS-CoV-2 and dengue, including laboratory evidence that some cross-reactive antibodies can enhance dengue virus infection under experimental conditions.
However, laboratory antibody-dependent enhancement does not establish that Covid infection or vaccination causes clinically meaningful enhancement of dengue disease in humans.
Human epidemiological evidence remains limited, and more research is needed.
Still, I wanted to share what the research shows thus far.

First raised in 2022, it was hypothesized that dengue antibodies could either help cushion a Covid infection (making it milder) or may lead to ADE and thus potentially worsen outcomes.
A January 2026 study published in Frontiers in Immunology found the more concerning of the two: that antibodies to Covid acquired from natural infection in humans or through experimental immunization in animals were cross-reactive with the DENV-2 strain of dengue, and had the potential to enhance DENV-2 infection in cells. The team went further than most earlier work, confirming the effect not only in cell cultures but also in a live-animal model. Mice infected with SARS-CoV-2 three weeks before a dengue challenge showed measurably higher dengue viral loads in blood, liver, and spleen than mice without prior Covid exposure. Essentially: Covid infection may lead to elevated risks and symptoms in subsequent dengue infections.
A related finding from researchers in Taiwan, also published in Frontiers in Immunology in late 2025, is that Covid vaccination (not just infection) can also generate cross-reactive dengue antibodies that were able to trigger dengue ADE in laboratory tests, even where anti-dengue IgG levels were low. Alongside the January 2026 paper, could cross-reactivity extend to anyone carrying Covid antibodies, however they got them?
A separate pilot study published in January 2026, also in Frontiers in Immunology, looked beyond the lab, profiling dengue patients. It found that those with a prior Covid infection showed a distinct pattern of immune dysregulation, skewed toward a Th2-type response (sigh, can confirm), with signs of enhanced viral replication compared to dengue patients who had no Covid history. It is a small pilot study, but interesting to see patient research alongside the lab and animal data.
A November 2025 paper published in The Lancet Regional Health – Western Pacific, “Risk of dengue following prior SARS-CoV-2 infection: a population-based cohort study“, was a large population-based study in Singapore. It found a modest increase in the risk of documented dengue infection during the months following a Covid infection, but this observational finding does not establish that Covid causes antibody-dependent enhancement or more severe dengue.
But what about the inverse?
An earlier 2025 paper entitled “Effects of Recent Prior Dengue Infection on Risk and Severity of Subsequent SARS-CoV-2 Infection: A Retrospective Cohort Study” looked at a national population-based cohort of adult Singaporeans and found increased risk of SARS-CoV-2 infection, and worse Covid outcomes, among people who had recently had dengue. As with the studies above, this is an observational finding. It shows an association, not that dengue causes more severe Covid — but the authors note it matters in tropical countries where dengue and Covid outbreaks overlap.
Regardless of what further results show, it’s important to make sure you’re testing appropriately to know whether it’s dengue, Covid, or something else so that you can treat appropriately.

Dengue and Covid-19: two sides of the same coin
Dengue led to Mast Cell Activation Syndrome (MCAS) for me
While I addressed the concept of “long dengue” above, for me the fatigue, the hair loss, the joint pain, and the depression and anxiety I spoke of in my piece about chronic pain was markedly different from my friends’ experiences with dengue.
Many friends had an infection and got over it just fine. However, with an existing autoimmune condition (celiac), the infection was really difficult. For others, they had a few months of problems but are fine now.
I never got back to normal.
It has been over two decades, and the infection plus my stubborn unwillingness to stop travelling and rest longer-term led to an inflammatory immune condition called mast cell activation syndrome, which is similar in symptoms to long Covid descriptions. I even had what people are calling “Covid toe” for years.
At the time of my infection in 2013, I thought I’d just take time to get better. Instead, my immune system got more and more reactive and in 2017, I had a diagnostic lumbar puncture done that led to a spinal CSF leak that is still ongoing.
Like Covid for some people, dengue changed my body and immune system and I became reactive to environmental and other triggers that I’d spent 40 years of my life having no issues with. I now have many new reactions to foods, smells, even the sun. I go into anaphylaxis on the regular. Vascular changes abound, and I have become intolerant to hot or very cold weather; my toes go blue in the shower and my circulation is affected by environmental triggers as well — to the point where I lose feeling in my extremities as they swell when exposed to them. This is especially bad during pollen season, and “smoke season” (either due to wildfires or heating homes with woodsmoke, which is common in my part of Canada).
Dengue infection is known to activate mast cells and involve mast cell mediators during acute infection, and these pathways are being investigated as part of dengue’s immunological response. However, I do want to be clear that dengue has not been established to cause chronic mast cell activation syndrome in the literature. My own trajectory of developing persistent symptoms after dengue is a personal clinical experience, not evidence that dengue causes MCAS in everyone.
My story is part of why I wanted to write this page, just as it has led to many other resources over the years.
Additional reading about dengue fever:
- If you want a first-person account that isn’t mine, this January 2026 piece in Yale Climate Connections is worth a read. The author got dengue in Baja California Sur in September 2025 after a run of tropical storms, and only realized that something was very wrong mid-flight when the plane was over the Pacific. He ended up hospitalized on day seven as his platelet count dropped. He writes about how dengue is now the world’s fastest-spreading mosquito-borne disease, and similar to how I feel is very worried about what this will mean for us.
- For those with journal access, a good overview of dengue as a disease is from “Dengue” in The Lancet, published February 2024 and written by researchers at the CDC, NIH, and the University of the Philippines. It covers virology, immune response, why some people get severely ill, and the vaccine landscape in one place. It’s the paper nearly everything else cites, and it’s readable if you’re willing to go slowly. In addition, Nature published a piece entitled “How mosquitoes are conquering the world — in four charts”, which does exactly what the title promises.
- The WHO released newer clinical management guidelines in July 2025 covering dengue, Chikungunya, Zika, and yellow fever together. This is the document you may want to hand a local physician if they are unfamiliar with dengue. The WHO also shared a global preparedness and response plan for dengue and other Aedes-borne viruses. Around four billion people are currently at risk of arboviral infection, a figure expected to reach five billion by 2050.
- There are also the Pan American Health Organization guidelines that I referenced above, about the diagnosis and treatment of dengue, Zika, and Chikungunya (PDF, 159 pages).
- CDC has a ‘Clinical Features of Dengue‘ page as well, which notes that approximately 1 in 20 patients with dengue progresses to develop the severe, life-threatening disease called severe dengue.
- A 2019 piece in the New York Times, “The Mosquitoes Are Coming for Us“, goes into history as well. From the piece: “The mosquito and her diseases have accompanied traders, travelers, soldiers and settlers (and their captive African slaves) around the world and have been far more lethal than any manufactured weapons or inventions.”
- A 2019 article about how mosquitoes “slaughtered our ancestors and derailed history” in the New Yorker notes: “Along with smallpox and influenza, mosquito-borne diseases led, by Winegard’s estimate, to the deaths of ninety-five million indigenous inhabitants of the Americas, from a pre-contact population of about a hundred million.“
- What about vaccines? For many years, there was no safe vaccine available. Previously, the Sanofi vaccine, Dengvaxia, rolled out with problematic results. Sanofi has since announced it will stop manufacturing Dengvaxia in 2026 because of low global demand. In December 2022, though, a dengue vaccine developed by Japanese drugmaker Takeda Pharmaceutical Co. was authorized for use in the European Union, called Qdenga (TAK-003). It is licensed in several countries, with the authorized age range varying by jurisdiction. WHO currently recommends its use in children 6 to 16 years old living in areas with high dengue transmission. Qdenga is still not FDA-approved in the USA. Takeda’s vaccine is based on a DENV-2 virus, with DNA from the other three serotypes added in so it protects against all serotypes. Data from Takeda’s main trial showed that the vaccine induces immune responses (varied ones, depending on the person’s immune system) against all four dengue types. A third vaccine, Brazil’s single-dose Butantan-DV, was created via the same NIH-developed parent strain as India’s DengiAll vaccine candidate. This vaccine was approved by Brazil’s ANVISA in late 2025 and rolled out from February 2026 — but Brazil temporarily suspended the rollout in June 2026 out of caution. The Qdenga vaccine’s use in Brazil is unaffected. At issue with dengue vaccines generally is how long immunity and antibodies last. More research will hopefully give us this answer.
- In 2023, pharmaceutical company Janssen shared promising data on JNJ-1802, an antiviral drug that is aimed at preventing dengue and is taken orally (in pill form). While likely not feasible to give to everyone in dengue-filled areas, should these data pan out in further trials, it will be an option for travellers much like anti-malarials.
